
Here is a blog entry from the research site on wellness incentives. It is a good piece.
Perhaps targeting on how to drive wellness needs an atribute of the segmentation model to be career path or industry…food for thought.
 August 23, 2007
 0 Comments
Here is a blog entry from the research site on wellness incentives. It is a good piece.
Perhaps targeting on how to drive wellness needs an atribute of the segmentation model to be career path or industry…food for thought.
August 23, 2007 0 Comments
I have no idea how someone who doesn’t understand the internal working of the healthcare system gets things done. I have trouble when I understand it.
A few months ago, I had an issue with a prior authorization for an Rx for my son. I paid cash and then knew to send it in via a paper claim. It was still rejected. Fortunately, I know you can appeal twice and then formally a third time. It took two appeals and several “discussions” with the call center staff, but I got it fixed.
Today, it happened again. I had changed something on our plan and eligibility got mixed up so my Rx rejected. When I called, the managed care company said my family was all eligible. When I explained what happened, they informed me that prescriptions were a different eligibility file that they weren’t looking at. (Like I should know to ask this.)
They then explained that my employer must have submitted the wrong paperwork. I said that was impossible since I did the paperwork myself. I also explained to the agent that since the managed care eligibility was right then it was a data entry issue on the pharmacy side for them. She tried three times to tell me to talk with my employer. (Only because I understand the process did I refuse.)
She finally went away for 20 minutes. (I was sure she was just sitting there laughing at me.) When she came back, she admitted that they had made an error and needed to fix the eligibility data. Of course, it couldn’t be done tonight, but it could be done in the morning.
If I didn’t know how data was sent and the processes, I would have been chasing my tale with my employer and TPA for days. I feel for all of you that don’t know these things.
August 23, 2007 0 Comments
I was reading a new blog tonight on healthcare research. Boring…NO. This is a good blog call Health as Human Capital Foundation.
One of the entries was about misalignment of incentives. It is an interesting point. It made me think of a typical call center metric called First Call Resolution. This measures how many customer issues are resolved the first time they call the call center. Wouldn’t it be wonderful if this was true in healthcare? How many people have had to go to their primary care physician, a specialist, another specialist, etc. to try and figure out what’s wrong with them?
August 23, 2007 0 Comments
I was a little surprised to see that the state of Minnesota is leading the pack in requiring that physicians use electronic prescribing by 2011 if they contract with the state employees. In theory, using an eRx software product like Purkinje, Allscripts, or Prematics, should reduce errors and save patients money (more generics, more mail).
The key question that I always had is that the big value here is by driving edits that today happen at the pharmacy to the point of care (POC). Will a physician want to deal with step therapy, drug-drug interactions, drug not covered, and other messages in the middle of their patient visit? On the one hand, they deal with it regardless since they get called by the pharmacy…but it changes their workflow.
And, how do patients feel about physicians with their face in a PDA or a laptop? Not that all doctors have great bedside manners anyways. Wouldn’t it be great if physicians could just dictate prescriptions by voice and enable pharmacists to move patients to therapeutic alternatives that were clinically appropriate and saved patients money. A few states allow this, but we are a long way away.
Very few prescriptions get written with software solutions today. Adoption has been hampered by failed products and failed companies. Even physicians with the technology often stop using it quickly.
August 23, 2007 0 Comments
Since many in the industry miss the semantics here, I am sure those of you that are consumers could benefit from a couple of points here.
If you are on a brand drug, there are two types of generic opportunities to consider. One is a chemical substitution. In this case, the patent has expired on the brand and the same chemical entity is available in a generic form. In many cases, unless your physician marks DAW (dispense as written), you will get the generic drug (or pay for chosing the brand drug). The only time I would ever hesitate to do this is on NTI (narrow therapeutic index) drugs where the active ingredients are titrated to your blood – e.g., coumatin.
The other type of generic savings opportunity is a therapeutic substitution. In this case, there is a generic drug that is therapeutically equivalent to your drug but NOT the same chemical entity. For example, if you take Lipitor, you might have the same ability to manage your high cholesterol using generic Zocor which became available about a year ago. In most drug classes (or for most conditions), there is a generic drug available. Many of these were the former blockbuster drugs in this category.
It is worth talking to your physician or pharmacist about this. Additionally, it is worth going to your managed care or PBM website and using their online tools to look up chemical and therapeutic switch opportunities.
August 22, 2007 0 Comments
It’s interesting to me that NY has gone after Aetna, Cigna, and UHG to not publish and use their physician ranking in their state. I agree that we need information about how these ranking are created. And, it is important that the lowest cost physician is not the highest ranked physician (necessarily).
But, it seems like a call to cooperate and drive standards that benefit patients is better than simply trying to close down the programs.
I think you need an Economic Value Added (EVA) type summary metric that aggregates a series of key data points for physicians. In my humble opinion, those metrics need to address:
Just some initial thoughts. It isn’t an area I have spent a lot of time on, but it is one that is important. Consumers would like to know how to compare physicians and choose one that meets their needs (which may vary by severity of the disease).
FYI: Here is a good blog entry by another author on this topic of metrics.
You can also look at the Physician Quality Reporting Initiative metrics.
August 22, 2007 0 Comments
There is a new study out about consumer directed health plans by Watson Wyatt and RAND Corporation. The multi-year study was jointly funded by the California HealthCare Foundation and the Robert Wood Johnson Foundation. Copies of the research brief, “The CDHP Implementation Experience with Large Employers,” are available at http://www.watsonwyatt.com/cdhp.
Not surprisingly, it points out that companies need to educate employees about how to be responsible for their care and give them tools on cost and quality. These need to be easy to use and easy to understand.
Here are a few of the key points:
“Employers have high expectations for CDHPs,” said Roland McDevitt, director of health research at Watson Wyatt and co-author of the study. “While their early experiences are favorable, the success of the plans will ultimately hinge on whether employers can provide employees with decision support tools that will empower them as engaged consumers.”
August 22, 2007 2 Comments
 I had the opportunity to read Medco‘s Drug Trend Report yesterday on the plane. I have read Express Scripts many times (and helped write and edit several sections). I saw several graphs I thought you might find interesting on the general market.
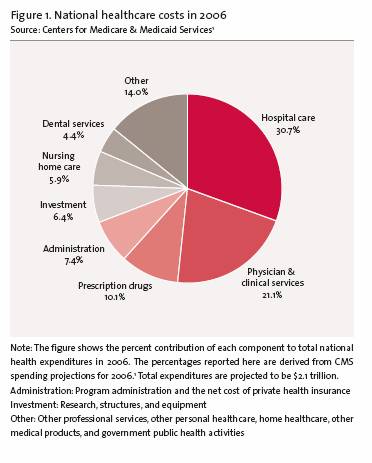
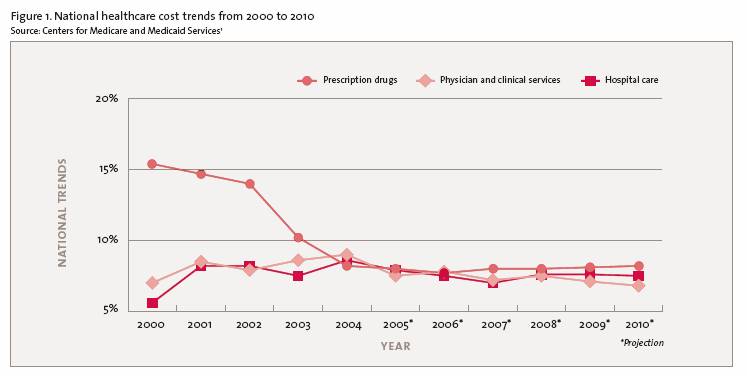
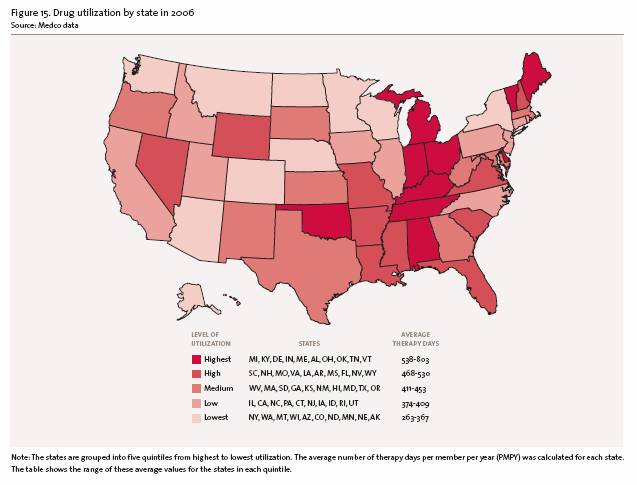
August 22, 2007 0 Comments
I saw a summary of this JD Powers report in the medcoExtra (internal weekly publication). I think the data is interesting so here is what they reported:
August 21, 2007 0 Comments
Why don’t insurance companies cover selective OTCs (over-the-counter)? I always heard clients talk about opening pandora’s box. If I cover one OTC then I have to cover aspirin and vitamins. Hopefully, us consumers aren’t stupid enough to look a gift horse in the mouth.
But, I like to make rational economic arguements. So, let’s look at the math around Proton Pump Inhibitors (PPIs) such as Nexium. If a client covers these, they probably pay somewhere around $100.
But, whatever the assumptions, it has to be cheaper for them to give the OTC product which might cost $20, to the members for free. Why not?
August 18, 2007 0 Comments
I always like to watch other blogs and look for interesting entries. Here are a few good ones that you might enjoy:
August 16, 2007 1 Comment
I can’t weigh in on the quality of care issue that surrounds the mini-clinics that are popping up all over the country (but here are a few facts). But, from a convenience perspective, I like the concept. They still aren’t open enough hours for me. Why not focus on 5-9am and 5-11pm which always seems to be when things go wrong.
I came across a good article with some facts on the trend from 8-11-07:
There is even a Convenient Care Association that you can go to learn about the industry.
At the Health Business Blog, David mentions a site called Healthcare311.com where you look up the nearest clinics. At least I think it is supposed to. It crashed for me multiple times.
August 16, 2007 0 Comments
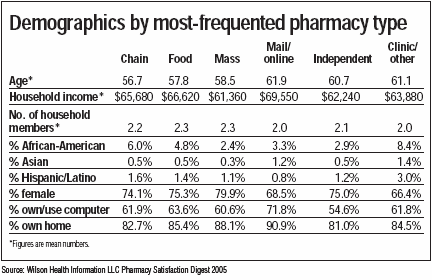
Anyone with prescriptions knows there are different pharmacy types – independent, online, mail order, grocery, and chains (e.g., Walgreens). Each have different attributes. The biggest question is always why one choses one over the other, whether there is a difference, and who is the most probable to chose one over the other. In February 2005, Drug Store News put out what is probably one of the best studies on this. It shows segmentation, reasons people chose one pharmacy over another, and other good data. The graphical version is available as a PDF for $5 here. Otherwise, you can read the plain text version. One of the central points is that as consumers want convenience and chains implement drive-throughs then they are playing into the mail order trend. They are disintermediating the pharmacist-patient relationship.
“In general, one of the things we’re seeing is that consumers are spending less time overall interacting inside the store,” Wilson said. “Not only is mail pulling them away, but [as] these drive-throughs increase dramatically … customer interaction seems to be shifting away from a more personalized approach to more time-saving and convenience methods.”
Abroad (from what I understand), the pharmacist and pharmacy play a more central care role with regards to the patient. I think pharmacists that have time try to do that today, but the model is not set up for that. This might be a model that CVS pursues with the blending of Caremark and MinuteClinic. The study said that only 11% of people know the first name of their pharmacists. Do you? Mine are Renee and Mark. I know them both well.
Here is one of the charts you will find that shows some variance across pharmacy type. It didn’t show any statistical values so I don’t know if the differences are meaningful.
August 16, 2007 4 Comments
I always like to try to think out-of-the-box and have tried to see a future where tools like Second Life will affect healthcare. (I haven’t played Second Life which is a virtual reality world being used for all types of things. Look into some of the articles or blogs about what IBM is doing with it.)
I was reading a blog entry yesterday on DigitOwl about some future technologies called semacodes, MyVu, and d’fusion (see below) and then saw a new entry this morning in the eHealth blog when an idea started to form.
Put simply, Semacodes are machine-readable codes that contain URLs. Think “cooler barcode” and you’re on the right track. Almost all advertising will carry Semacodes, enabling consumers to photograph them to connect to information instantly via a mobile device.
The second piece of technology Tom highlights in his blog is MyVu; “funky Robocop-style sunnies” that are already available at apple.com. MyVu glasses plug into your video iPod to create a virtual big-screen within the “real space” in front of you.
The third piece of Tom’s technology pie is something called d’fusion (no, it’s not a fancy French hair product). D’fusion is a software that will allow you to create “augmented reality”. Put simply, a merging of real time, 3D objects/characters with live video.
In the future, could we simply pause when we felt sick, put on our MyVu glasses to create a virtual big-screen wherever we are, use d’fusion technology to enter a Second Life type of environment, and see a whole series of MDs, specialists and others in real-time. They could be anywhere in the world. They could give you an Information Prescription and/or a real prescription (digital of course) with a series of semacodes on it that could be used to take you to other virtual environments or content locations. You could then stop on your way home at a kiosk to pick up any physical drugs or products you needed.
Of course this only works with the advent of Smart Devices that could be used to take all the physical measurements that a clinic, nurse or MD would take, but that seems very feasible. A device injected inside you which constantly monitors blood pressure, temperature, and tests your blood could address this and push your data to a PHR or other data source that the virtual physician could tap into.
Great. No waiting. Instant gratification. No travel. Access to the best care in the world. Links to lots of information. Seems logical to me. Already, people are trying telemedicine and telepharmacy.
August 15, 2007 0 Comments
One of the key programs we used at Express Scripts to manage trend was Step Therapy. What this means is that a patient is required to use a less expensive drug (typically a generic) prior to using a more expensive drug. A day-to-day example of this is with antibiotics. Anyone with kids knows that you start your child on a generic antibiotic and if that doesn’t work you escalate to a stronger (and more expensive) product.
Step Therapy has two challenges. One, consumers got “rejected” at the Point-of-Sale (POS) (i.e., the pharmacy) and were upset they couldn’t get the drug their doctor prescribed. Two, how do you handle programs like this (that are effective) with CDHC where the consumer is responsible for managing their own money and edits are typically frowned upon.
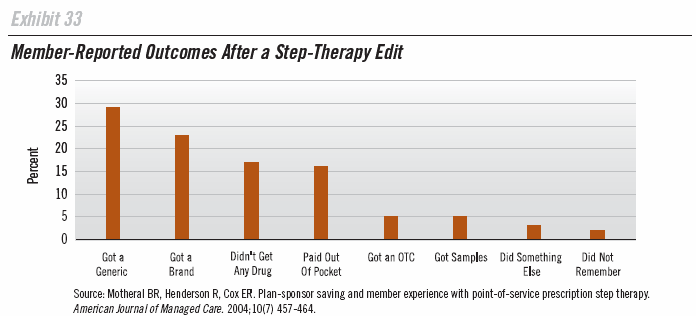
Patients generally don’t understand plan design and edits and don’t know what to do. As you can see from the Express Scripts 2004 Drug Trend Report (pg. 121), a material amount of people filed no claim (great savings) but did take action (i.e., no negative clinical outcomes identified). We developed a rapid response program to inform them what to do to get their drug covered which seemed to help.
But, what do you do in a consumer driven plan where you just have a high deductible. I for one advocated that I would like edits that forced me to save money. Perhaps, I needed an override code, but I wanted to know when and how to save money. Left to my own devices and having to research every prescription would be a burden.
I think this still remains to play out, and I am sure there are lots of opinions here.
August 15, 2007 0 Comments
I mentioned the Top 100 Healthcare Blogs a few weeks ago. Well, I made it to the honorable mention at number 366. So, if you like what you read here, help me move up the rankings by:
Thanks.
August 15, 2007 1 Comment
After posting the note on Sermo yesterday, I began wondering about a patient’s ability to influence their physician. The best study I have seen on this topic was around Direct-to-Consumer (DTC) advertising on brand drugs. The FDA did a study a few years ago that showed how that information influenced the physician-patient relationship. It is a good read (if you like studies).
But, what do you do when you know about some type of online resource for your physician? Can you influence them to go out and research your disease state? Will you even push your physician on his or her knowledge?
I think this is definitely influenced by generational issues. This is a sweeping generalization, but I generally see older people have more deference towards people like physicians. I think some of that is beginning to change as people bear more costs and responsibility for their healthcare. But, younger people (who are not the sick ones generally) have a greater willingness to challenge those in authority (good and bad).
We faced this issue a lot at Express Scripts in trying to drive generic drugs and mail order. Eventually, we created a “Physician Kit” that the patient could complete online and print to take to their physician. It was presented by the physician, but it had the backing of the provider.
August 14, 2007 0 Comments
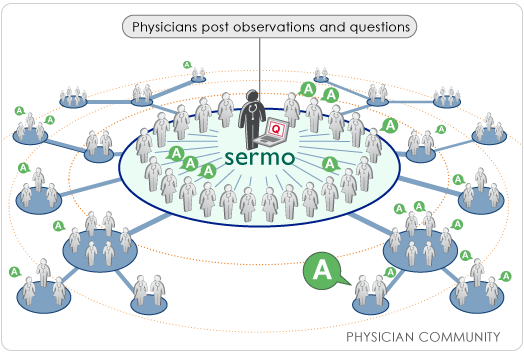
I saw this mentioned in the HealthNex blog and thought I would add it here. I was thinking earlier today about the power of social networking from a patient perspective. It is helpful (and potentially misleading) to hear from peers when you have a chronic disease. They can provide you with experiential data that helps you understand. They can also direct you to information sources.
For people with more fatal diseases, they can serve as a support function. Sermo, on the other hand, is a networking tool for physicians to help them share clinical experiences with other physicians. Here are a couple of examples of some postings (I can’t see everything since I am not an MD):
How often do you people develop fatigue and/or myalgias while on a statin? does it negate use of other members of this family? if so, what would your next drug choice be in the setting of a patient with high ldl and low hdl?…
this is a 65 y old woman diagnosed about 3 months ago with a right orbital grade II/III follicular lymphoma (lacrimal gland excised ). patient had a staging workup including PET scan and bone marrow biopsy which were negative ,that was after surgery….
This is definitely the power of Health2.0 where people can collaborate and share information using web tools.
August 14, 2007 0 Comments
I was looking for something else on the Aetna site and stumbled across this picture in their latest investor presentation (Morgan Stanley Global Healthcare Unplugged). For those of us looking at consumerism, I think this is a good snapshot for competitive intelligence.

It hits all the key buzzwords – optimizing health, quality, affordability, literacy, transparency, and evidence based. The proof is always in the actions, but this is what you want your MCO to be discussing. The key challenge in all of this is bringing information to the consumer in digestible amounts and in a format and language that they can understand.
August 14, 2007 3 Comments
I use Google all the time. I have been very interested to see pieces of information around Google Health. Will it compete with WebMD and Revolution? Will it create new tools like a PHR? How will it leverage its technology to improve healthcare?
I found their announcement of their board several months ago interesting. A good mix of people – MDs, employers, academic facilities, researchers. I didn’t notice many technologists which surprised me. There are numerous start-ups with MDs or RPhs or other health professionals running them.
More to come, but a company with great resources that understands how to innovate and seems to have a social conscience could make a big difference here. You can go read a speech by Adam Bosworth at Google about this.
August 14, 2007 0 Comments
The Robert Wood Johnson Foundation has funded something called the Consumer Voices for Coverage which begins in 2008.
The need from the project comes from the publication of Consumer Health Advocacy: A View from 16 States by Community Catalyst in October of 2006. This calls for consumers to be active in protecting and expanding healthc are access. In order to be effective, consumers need to organize into state advocacy networks with the ability to:
I must admit to never being much of an activist, but I certainly support the concept of people being active to support their cause. And, of the many causes out there, access and care for people is a good one. In a wealthy country like the US, it is a shame to see people dying and in pain for simple reasons like lack of access.
Unfortunately, many Americans probably don’t realize how good we have it here. Even those without have TVs and clothes. Go to a 3rd world country and spend some time with the poor. It will radically change your opinion.
August 14, 2007 0 Comments
I find it interesting that all the financial magazines I read talk about how life expectancy is going up in the US. They talk about the need to plan for 30+ years of retirement money.
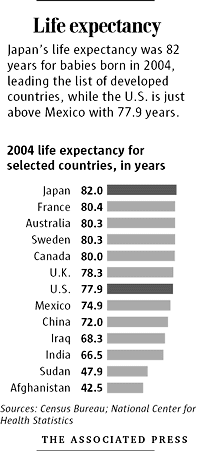
At the same time, all the healthcare articles I read talk about life expectancy in the US (although at an all-time high) dramatically lags behind 41 other countries…even though we spend the most on healthcare. You can read the AP article here. It makes some interesting points blaming the difference on obesity (2/3 of Americans are overweight), the fact that we have 47M uninsured Americans, and our horrible rate of infant mortality (6.8 out of 1,000).
Here is the chart from the article:
August 10, 2007 0 Comments
I was pleasantly surprised this morning to learn about RxWiki.com. This is a website by pharmacists to provide consumer information about drugs, OTCs, and other products. Certainly, for those practicing pharmacy (versus in the ivory tower), they should have some good first hand experiences to share with patients.
I think about when I first started seeing advertisements for Alli (diet drug). When I asked a pharmacist about it, he said it was great as long as you eat no fat. He said you couldn’t make it from taking one bite of a McDonald’s hamburger in your car into the bathroom at McDonald’s fast enough to avoid an accident. Doesn’t sound appealing to me. Why not just give up fat?
I wonder if we will ever see a MDWiki (somebody already has the URL). These collaborative tools are great for allowing people to share information with the general public. Hopefully, they have the right disclaimers so they don’t ever have some frivolous lawsuit because I think consumerism is only going to take off when information is generally available with some quality assurance process. We need to trust the information but have it relayed to us in straightforward, non-legalese.
August 9, 2007 0 Comments
The more I learn about automated call technology the more I wonder why people don’t use it as much as letters. Obviously, there are telemarketing laws. And, I think many people think of calls as only being done by humans and being expensive.
But, imagine the following differences and benefits:
Obviously, e-mail is the cheapest medium, but our culture is rapidly becoming overwhelmed with e-mail. You have some of the same benefits, but you can’t modify during the interaction. And, in healthcare, there is limited information you can push to a patient. In most cases, you are asking them to click through a link to go to a secure website to receive information. With letters, you assume it is secure since it is addressed to them. With automated calls, you have them verify who they are based on a few points of reference (name, DOB, member ID).
August 9, 2007 0 Comments
In the spirit of advocating for the patient, I think one of the key things missing at many companies is culturally specific communications. The simplest solution here is multi-lingual. Now that nearly 1 in 10 counties in the US have a majority of minorities, this is important (USA Today 8/9/07).
Of course, I always hear the question back of how do I track this. Will people self-identify into a cultural group? It depends. Do you have anything to offer them? Can you articulate value to them?
If I speak a different language as my primary language and you offer me communications in my native tongue, I would likely be happy to request it. Can you track it when I request it? Aquent appears to be a company focused on this within the healthcare space.
This can also manifest itself in color selection. For different cultures, a certain color can mean different things which might affect your brochure creation. (see article) Of course, you need to be able to do mass customization of your brochure rather than print 7M in one run.
With hispanics expected to represent 21% of the US population by 2020, it will be important to understand this segment and how to communicate with them. Here is a good article on this. I have seen studies that show they respond at a higher rate than other segments to both letters and direct calls. Shouldn’t that be important?
The point here is that if you really care about the patient and their health wouldn’t you want to push information to them in a language they care about; using colors that evoke action and emotion; and using words and frameworks that they understand.
August 7, 2007 0 Comments
There are a few places that I always go for information. I thought I would share them:
More to come, but I found myself going to the same site multiple times today and jotted down a few URLs that I find as common tools.
August 7, 2007 4 Comments
I find the whole concept of Medical Tourism fascinating. The fact that it can be less expensive for someone in the US to fly to a foreign country and get an operation done is logical while also amazing. When I was trying my start-up, one of my board members had a friend raising $2B to develop a medical center in Asia to bring people there for long-term surgery and recovery periods.
Business 2.0 had an article about medical tourism that predicted it would be a $40B market by 2010. A great opportunity?
Example from the article “GlobalChoice sent a patient to Punjab for a hip replacement that cost about $13,000, including airfare and a 20-day hotel stay. The estimated cost in the United States for the surgery alone? $40,000.”
I also found it interesting in a April 2007 Wired article called “Organs for Sale” to see the prices for transplants overseas (with much higher availability also).
My key point with blog (other than just interest) is that there is a market for companies to provide these services, insure the patient, manage the quality of care, and offer incentives (even for insured people) to get this care.
August 6, 2007 0 Comments
So what does BodyMedia have in mind…If you read this article from a few years ago, I think they are on to something. Can you put sensors in people’s clothes without changing the comfort of the clothes – probably? Can you link those sensors to data driven models to help drive behavior – sure? Will people wear the clothes, use the data, and change behavior – who knows?
The concept is right. Embedding technology into everything we do and using that data to push information to us at the right time is critical to changing behavior and driving technology enabled wellness. I love the picture below of their reporting. I get this from my GPS watch. I definitely intend to learn more about what they are doing.

August 6, 2007 0 Comments
Can incentives actually drive wellness? Why not? Why?
Incentives are powerful tools once you understand the healthcare consumer and how they react. Is the incentive a lower copay? Is it a free service? Lots of interesting models are going to come up. It has worked in other industries but can it work here.
I think a lot will depend on the segment of the market and what you are asking them to do. A old person (i.e., a MD worshipper) is unlikely to challenge their doctor and push for certain action. A younger person in good health (i.e., a Living for Today) is unlikely to respond to messaging about pre-screening and general check-ups.
Here are a couple of the things out there:
Another model which will be interesting is existing companies like Maritz which do loyalty programs and incentive programs for other industries. As they apply their skills to the healthcare market, it should allow this to take off faster.
August 3, 2007 0 Comments
I think the Information Therapy concept is a great way to think about consumerism and information in the healthcare space. I was recently reviewing a presentation by Healthwise which pointed out 3 Simple Rules:
Another place where you can learn more about this concept is at the Center for Information Therapy. From a health plan perspective, here is one of their white papers which will help you begin to conceptualize this.
The key here is that we should be able to use data to trigger information events that are personalized to people. This obviously needs to be actionable information that is in a format and uses terminology that patients can understand. There is a huge difference between data and information. Lots of data is sent to patients along with a typical “barfing” of information with no context or prioritization.
It is a great opportunity. Lots of healthplans and consumer sites are embracing this. As this gets refined and becomes mainstream, it can help drive wellness and a change in ownership for healthcare where consumers really feel responsible and can act responsibly for their care.
You can also look at Josh’s blog for more ongoing dialogue.


 WSJ Health Blog Drug Channels KevinMD Blog Health Populi e-Patients
 Contact me at gvanantwerp @ mac.com.
 Enabling Healthy Decisions
